

Selecting the Best Laparoscopic and Robotic Myomectomy Centres in India for Canadian Patients
Ten weighted criteria — but first, what Canada's own legislature has admitted on the record about non-cancer gynecologic care, and why India's leading centres offer a genuinely strong, fertility-preserving path forward.
In 24 years of guiding international patients into Indian hospitals, this exchange, drawn directly from an official Canadian legislative record, is genuinely revealing. It confirms two things plainly: that women's non-cancer gynecologic conditions, including fibroids requiring myomectomy, face documented, acknowledged wait-time disparities compared with cancer-related gynecologic surgery, and that even officials responsible for the system admit this data gap exists and deserves a genuine women's health strategy to address it. The legislator's own framing is worth sitting with: robotic surgical resources are being directed specifically toward gynecologic cancer cases, a genuinely reasonable clinical priority, but this means non-cancer conditions like fibroids, however significantly they affect a woman's quality of life, pain, fertility and daily functioning, are competing for whatever capacity remains after cancer cases are served first.
Healing Journeys of Canadian Patients
Key Takeaways
- The guide highlights an officially acknowledged gap in Canadian access to non-cancer gynaecological care. The page 1 graphic, drawing on an August 2026 Nova Scotia legislative record, notes that no wait-time data were currently published for gynaecological oncology and identifies a significant discrepancy in access to non-cancer gynaecological care, which includes conditions such as symptomatic fibroids.
- The guide emphasises that 32.8% of open myomectomies could potentially have been performed laparoscopically, according to the research cited on page 2. It also notes the reverse pattern, with approximately 15% of laparoscopic myomectomies potentially better suited to an open approach, showing why the decision requires experience in both techniques rather than automatically choosing minimally invasive surgery.
- Laparoscopic myomectomy is presented as technically demanding because the surgeon must remove fibroids while preserving healthy uterine tissue and future fertility. The guide states that leading Indian gynaecology centres perform high volumes of laparoscopic and robotic myomectomies, with minimally invasive, fertility-preserving surgery offered as a standard option where appropriate, alongside English-language care and JCI/NABH-accredited hospitals.
- The selection framework gives 55% weighting to the surgeon and 45% to the hospital. Surgeon assessment focuses on specific laparoscopic/robotic myomectomy volume, discussion of fertility goals, personal involvement in surgery and complication data. Hospital assessment considers minimally invasive surgery as a standard capability, fertility-focused recovery support, verified accreditation and a complete surgical record for the Canadian gynaecologist.
- The page 4 qualification table identifies MS/MD in Obstetrics & Gynaecology as the base specialist qualification, followed by a 1–2 year fellowship in minimally invasive gynaecologic surgery as the most relevant additional training. Four warning signs are also listed: recommending open surgery without discussing laparoscopic options, being vague about specific myomectomy volume, failing to discuss fertility goals and quoting a price before reviewing the patient's imaging.
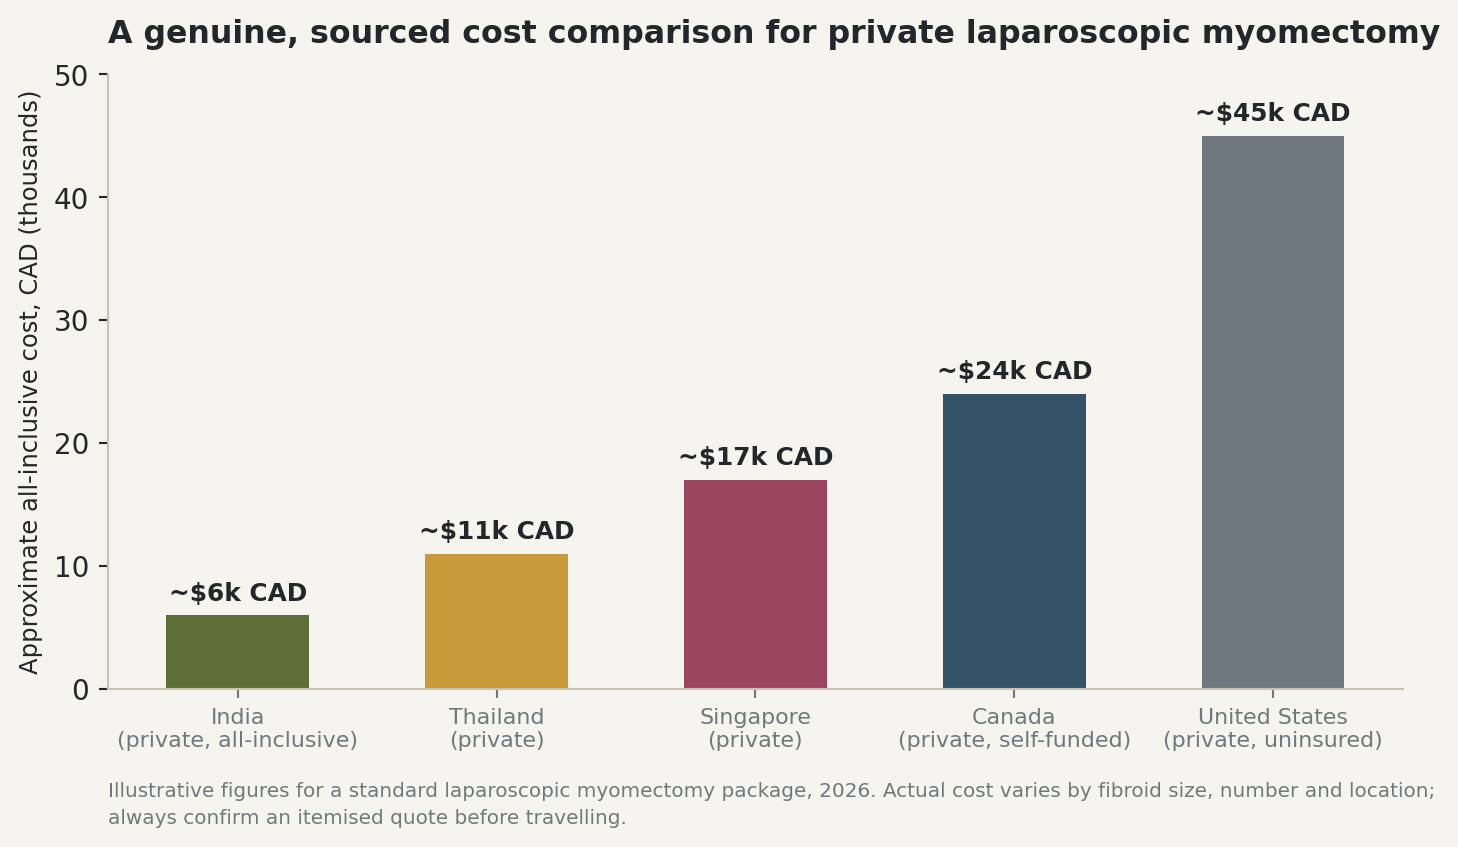
- The page 4 cost chart gives illustrative private costs of approximately C$6,000 in India, C$11,000 in Thailand, C$17,000 in Singapore, C$24,000 in Canada and C$45,000 in the United States for a standard laparoscopic myomectomy package. The guide states that actual costs vary according to fibroid size, number and location and recommends obtaining an itemised quotation after imaging review.
Quick Facts
- Treatment
- Laparoscopic & Robotic Myomectomy
- Patients
- Canadian Patients
- Purpose
- Fibroid removal while preserving the uterus and future fertility
- Key Specialist
- Gynaecologist / Minimally Invasive Gynaecologic Surgeon
- Selection Weighting
- 55% surgeon / 45% hospital
- Base Qualification
- MS/MD Obstetrics & Gynaecology
- Advanced Training
- 1–2 year fellowship in minimally invasive gynaecologic surgery
- Key Assessment
- Laparoscopic vs open suitability
- Fertility Check
- Patient's fertility goals should directly influence surgical planning
- Technology
- Laparoscopic and robotic techniques
- Hospital Check
- Fertility-focused recovery support and verified accreditation
- India Cost
- Approximately C$6,000
- Canada Cost
- Approximately C$24,000
- US Cost
- Approximately C$45,000
- Pre-Travel Records
- Pelvic imaging and fibroid mapping
- Treatment Timeline
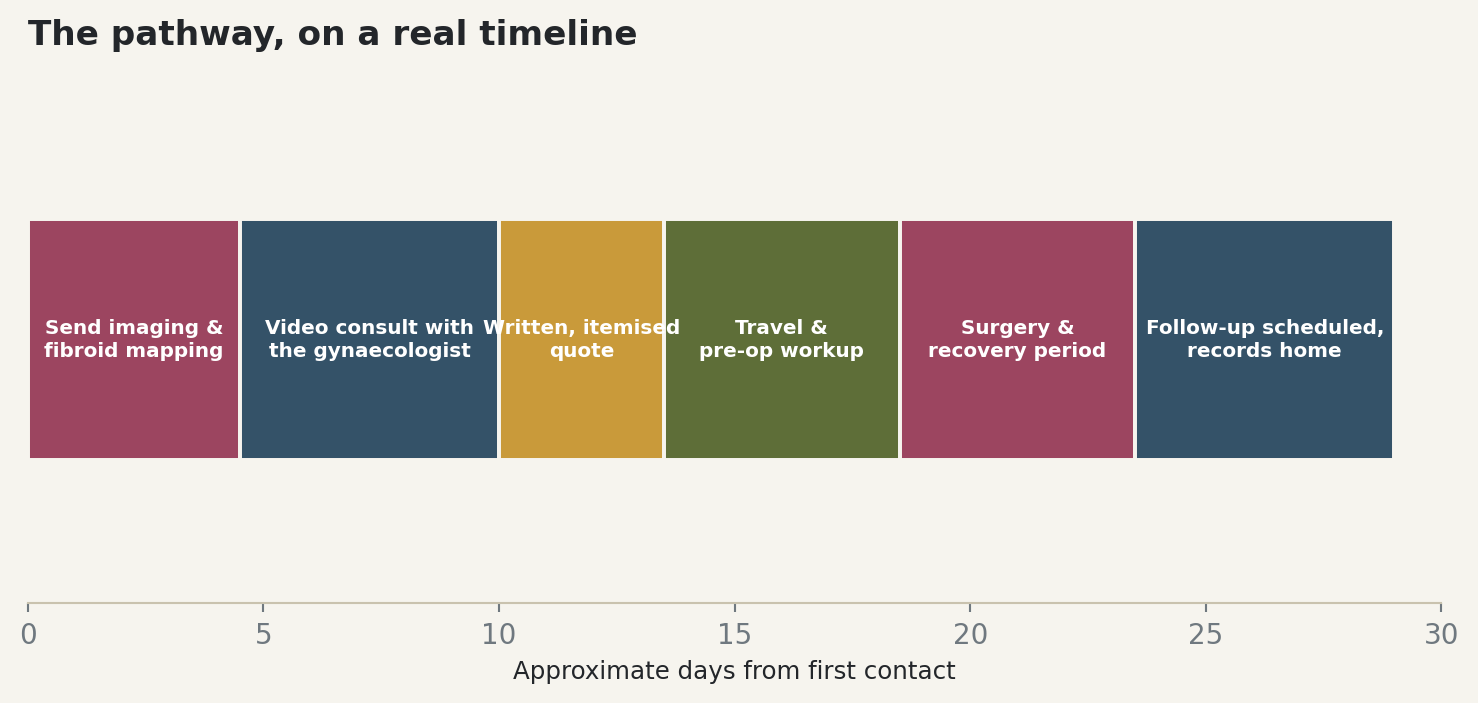
- Typically 2–3 weeks from first consultation
- Follow-Up
- Canadian gynaecologist
- Key Warning
- Avoid centres that recommend open surgery without explaining minimally invasive options
- Decision Principle
- Prioritise specific myomectomy expertise, fertility preservation and appropriate surgical approach.
- Author
- Dr. Dheeraj Bojwani
- Experience
- 24+ Years
In Brief
For Canadian patients considering fertility-preserving fibroid surgery, the guide recommends assessing laparoscopic versus open suitability on an individual basis, while giving significant weight to the surgeon's specific myomectomy volume, fertility-focused planning, minimally invasive expertise, hospital accreditation and recovery support. It also recommends arranging Canadian follow-up before returning home.

Myomectomy removes uterine fibroids while preserving the uterus and future fertility, a genuinely important distinction for women who want to keep their reproductive options open. This guide exists for patients whose gynaecologist has confirmed myomectomy is the right path, weighing where and how that surgery should happen.
This isn't a criticism of prioritising cancer care, which is clinically appropriate. It's a genuine, honest acknowledgment that this prioritisation has a real cost for the far larger number of women whose fibroids, while not cancerous, still cause genuine, significant symptoms including heavy bleeding, pain, and pressure that can meaningfully affect their daily lives and their fertility plans.
For patients facing this genuine, officially acknowledged gap, the case for looking seriously at India is a strong one: internationally accredited gynaecology centres with genuinely high laparoscopic and robotic myomectomy volume, fertility-preserving technique offered as the default approach, and treatment that can typically begin within two to three weeks of your first consultation, all at a fraction of the equivalent Canadian private cost.
A genuine, documented gap between what's done and what's possible
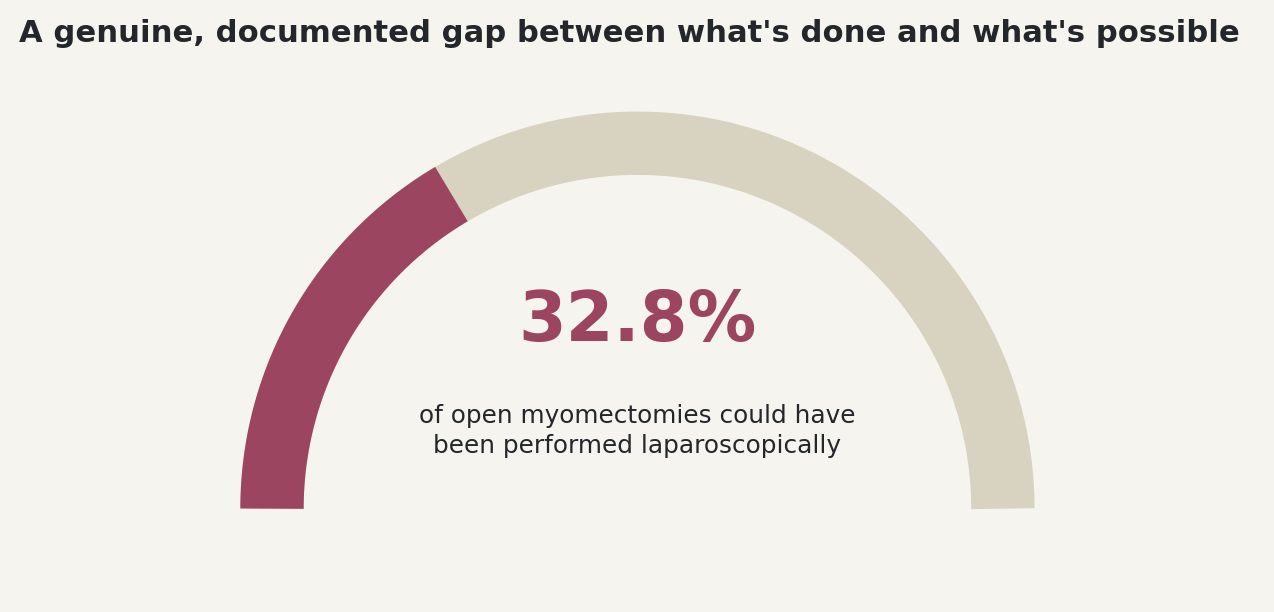
Get your full pelvic imaging and fertility goals together before your first overseas conversation. This finding matters because it shows the gap between open and minimally invasive myomectomy isn't simply about which cases are medically suited to each approach; a genuine, documented share of cases performed via open surgery could have been managed laparoscopically instead, with all the recovery and complication benefits that approach offers. This pattern reflects genuine variability in surgeon comfort and access to laparoscopic training, not a fixed clinical necessity.
This distinction matters enormously for recovery. Laparoscopic myomectomy is consistently associated with lower complication rates, shorter hospital stays, and faster return to normal activity compared with open surgery, precisely the outcomes most women hope for when choosing a fertility-preserving procedure in the first place. The same research found the reverse pattern too, roughly 15% of laparoscopic myomectomies may have been better suited to an open approach, confirming this is a genuine two-way judgement call requiring real surgical expertise in both techniques, not a simple default toward whichever approach a given surgeon happens to be most comfortable performing.
Laparoscopic myomectomy remains technically demanding in a way that genuinely rewards focused, dedicated experience. Working through small incisions with limited directions of traction, a surgeon must carefully dissect the fibroid from the uterine wall and then remove it, often requiring morcellation, all while preserving the uterine tissue needed for future pregnancy. This is precisely the kind of surgery where a surgeon's specific, sustained volume in this exact technique matters as much as general gynaecological surgical skill.
Why India specifically, not just “overseas”
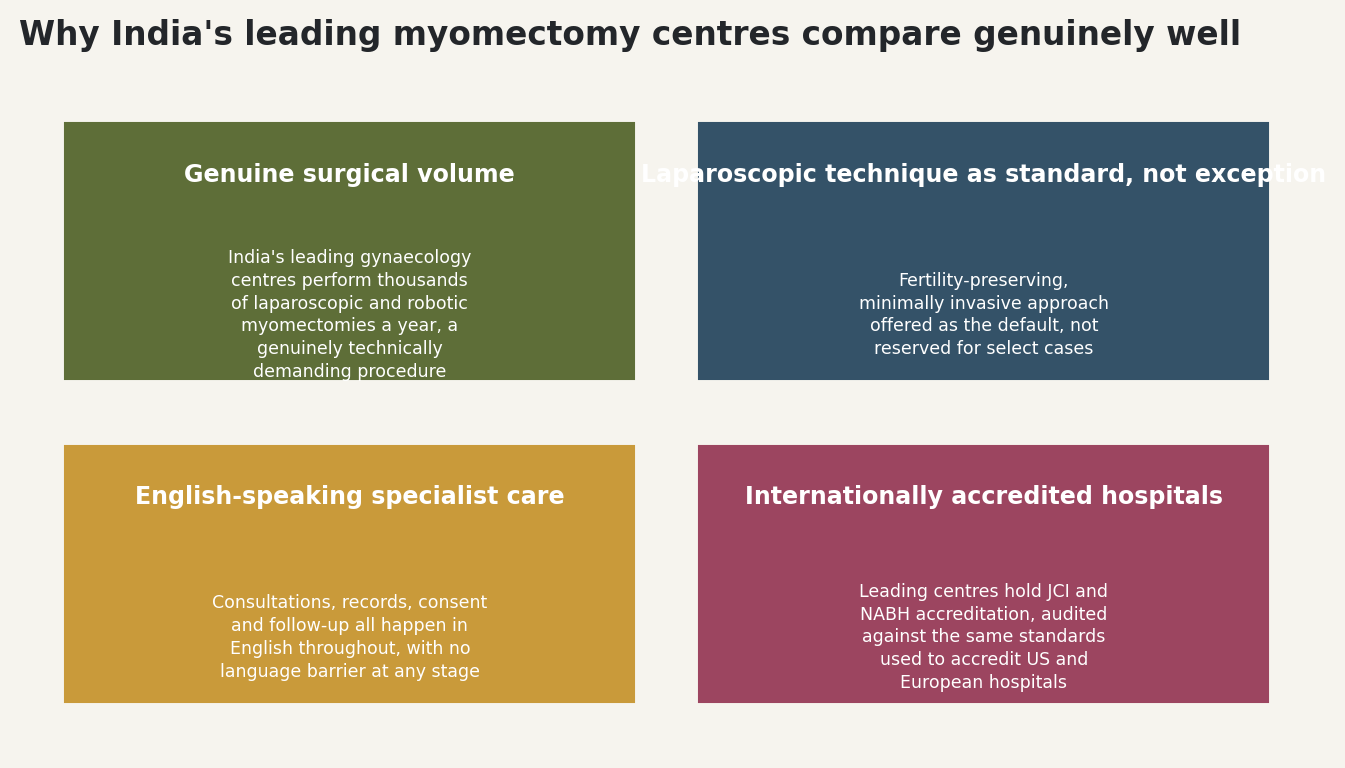
This is worth spelling out plainly, because “medical travel” can sound vague until you see what it actually means in practice. India's leading gynaecology centres perform a volume of laparoscopic and robotic myomectomies that reflects the scale of the population they serve, offering this genuinely more technically demanding, fertility-preserving approach as the default option rather than one reserved for select, straightforward cases. This is not a compromise reached for cost and speed; it represents genuinely deep, focused surgical experience in exactly the technique that the evidence favours.
Every consultation, medical record, consent discussion and follow-up letter happens in English, conducted by specialists trained to internationally recognised standards, and leading hospitals hold Joint Commission International accreditation alongside India's own NABH certification. Put together, this is genuinely comparable, fertility-preserving gynaecological care, at a fraction of the price.
Ten weighted criteria, out of 100
The same weighting that applies across this series applies here: the surgeon carries 55 points, the hospital 45. Part one, judging the surgeon: genuine volume in laparoscopic or robotic myomectomy specifically, an honest discussion of your fertility goals, whether the surgeon personally operates, and candid complication data.
| Qualification | Length | What it actually means |
|---|---|---|
| MBBS | 5½ years | The basic medical degree. A licence to practise, not a specialist qualification. |
| MS/MD (Obstetrics & Gynaecology) | 3 years | The base specialist qualification. |
| Fellowship in minimally invasive gynaecologic surgery | 1–2 years further | This is what matters most here. Dedicated further training specifically in laparoscopic and robotic technique. |
Part two, judging the hospital: laparoscopic and robotic technique offered as standard, a fertility-focused recovery plan, verified international accreditation, and a complete surgical record your Canadian gynaecologist can use.
Four Signals That Should Make You Pause
- Open surgery recommended without a genuine discussion of laparoscopic options. Ask directly why the minimally invasive approach isn't suitable for your case.
- Vagueness about the surgeon's specific myomectomy volume. General reassurance about “extensive gynaecological experience” is not an answer.
- No genuine discussion of your fertility goals. This should shape the surgical plan directly, not be an afterthought.
- A price quoted before your imaging has been reviewed. Nobody can meaningfully assess your case without seeing your specific fibroid mapping.
Canada-specific considerations most patients miss
Ask your Canadian gynaecologist directly whether your case is suited to a laparoscopic approach. Given the documented gap between what's done and what's possible, this question deserves a specific, honest answer.
Tell your Canadian gynaecology team early, not after the fact. Most are more sympathetic to a second opinion than patients expect.
Arrange your ongoing follow-up before you leave. Confirm your Canadian gynaecologist is willing to continue monitoring based on overseas surgical findings.
The Questions, in the Order You Should Ask Them
| Of the surgeon | Of the hospital |
|---|---|
| What is your specific volume in laparoscopic/robotic myomectomy? | Is laparoscopic/robotic technique offered as standard? |
| Why is this specific approach right for my case? | What fertility-focused recovery support is included? |
| Will you personally operate? | Which accreditation do you hold, and when was it last inspected? |
| What is your complication rate? | What does the final surgical record include? |
A closing word
Canada's own legislature has confirmed, on the official record, that non-cancer gynecologic care, including fibroid treatment, faces a genuine, documented wait-time discrepancy, with no published data even tracking it consistently. For patients facing that reality, the case for India is genuinely strong, not a fallback option: gynaecology centres with deep, current laparoscopic and robotic myomectomy volume, fertility-preserving technique offered as standard, and treatment that can typically begin within two to three weeks, at a fraction of the equivalent Canadian private cost.
In 24 years of guiding patients through exactly this decision, the pattern is consistent: those who look closely at what India's leading myomectomy centres actually offer, rather than assuming distance means compromise, generally come away reassured rather than anxious. Insist on a genuine laparoscopic-versus-open discussion, weight genuine surgical volume heavily, and travel with a written, itemised quote in hand.
If you would like a second opinion on your imaging, send it and I will look at it properly.
Frequently Asked Questions by Canadians about Laparoscopic and Robotic Myomectomy Centres in India
What is a myomectomy?
Myomectomy removes uterine fibroids while preserving the uterus, making it an important fertility-preserving option for suitable patients.
Why consider laparoscopic or robotic myomectomy?
The guide associates laparoscopic myomectomy with lower complication rates, shorter hospital stays and faster return to normal activity compared with open surgery.
Is laparoscopic surgery suitable for every patient?
No. The guide notes that approximately 15% of laparoscopic myomectomies may have been better suited to an open approach, so the decision should be based on individual fibroid characteristics and surgical assessment.
What does the 32.8% figure mean?
The cited research found that 32.8% of open myomectomies could potentially have been performed laparoscopically, highlighting the importance of access to surgeons experienced in minimally invasive techniques.
Which qualification should I look for?
The guide identifies MS/MD in Obstetrics & Gynaecology, followed by a 1–2 year fellowship in minimally invasive gynaecologic surgery.
How much does laparoscopic myomectomy cost in India?
The guide gives an illustrative cost of approximately C$6,000 in India, compared with C$24,000 in Canada and C$45,000 in the US.
What should I send before travelling?
Send your full pelvic imaging and fibroid mapping, together with information about your symptoms and fertility goals, for the initial consultation.
Why should fertility goals be discussed before surgery?
The guide stresses that fertility goals should directly shape the surgical plan, particularly when preserving uterine tissue and future reproductive options is important.
What should I ask the surgeon?
Ask about their specific laparoscopic/robotic myomectomy volume, why the proposed approach is appropriate, whether they will personally operate and their complication rate.
What should I arrange before returning to Canada?
Confirm that your Canadian gynaecologist is willing to continue follow-up based on the overseas surgical findings and take the complete surgical record home.
Sources
- Nova Scotia Legislature, Standing Committee on Health, Official Record, August 11, 2026 — nslegislature.ca
- Cooper et al., Opportunities for Change and Levelling Up: A Trust Wide Retrospective Analysis of 8 Years of Laparoscopic and Abdominal Myomectomy, 2024 — ncbi.nlm.nih.gov
- National Medical Commission — nmc.org.in
- National Accreditation Board for Hospitals & Healthcare Providers — nabh.co
Page Summary
This guide helps Canadian patients compare laparoscopic and robotic myomectomy centres in India, focusing on fertility preservation, procedure-specific surgical expertise, appropriate choice between minimally invasive and open surgery, hospital quality, cost and follow-up; it highlights a Canadian access gap for non-cancer gynaecological care and cites research indicating that 32.8% of open myomectomies could potentially have been performed laparoscopically, while approximately 15% of laparoscopic cases may have been better suited to open surgery. India is presented as an option with high-volume minimally invasive gynaecology centres, English-language care and JCI/NABH-accredited hospitals, with illustrative costs of approximately C$6,000 in India, C$24,000 in Canada and C$45,000 in the US.
Citation Block
| Field | Information |
|---|---|
| Topic | Best Laparoscopic & Robotic Myomectomy Centres in India for Canadian Patients |
| Treatment | Laparoscopic / Robotic Myomectomy |
| Patients | Canadian Patients |
| Treatment Goal | Fibroid removal while preserving the uterus and future fertility |
| Specialist | Gynaecologist / Minimally Invasive Gynaecologic Surgeon |
| Selection Weighting | 55% surgeon / 45% hospital |
| Key Qualification | MS/MD Obstetrics & Gynaecology + minimally invasive gynaecologic surgery fellowship |
| Volume Check | Specific laparoscopic/robotic myomectomy volume |
| Approach Check | Individual assessment of laparoscopic vs open surgery |
| Fertility Check | Fertility goals incorporated into surgical planning |
| Technology Check | Laparoscopic and robotic capability |
| Hospital Check | Fertility-focused recovery support & verified accreditation |
| India Cost | ~C$6,000 |
| Canada Cost | ~C$24,000 |
| US Cost | ~C$45,000 |
| Records Required | Pelvic imaging & fibroid mapping |
| Follow-Up | Canadian gynaecologist |
| Recovery Planning | Follow-up arranged before leaving India |
| Warning Signs | No laparoscopic discussion, vague volume, no fertility discussion, early pricing |
| Patient Pathway | Imaging/fibroid mapping → video consultation → itemised quote → travel/pre-op workup → surgery → recovery → records home |
| Key Decision | Prioritise specific myomectomy volume, fertility-focused planning and appropriate surgical approach |


Our Mission Statement
Our mission is to place patients at the centre of every healthcare decision by providing trustworthy, evidence-based, and unbiased medical information. We believe that informed patients make better decisions. Backed by personalised guidance from our experienced advisory team, we help patients understand their treatment options, compare them objectively, and confidently choose the path that best suits their medical needs and personal circumstances.
Patient Testimonials from Canada






Ready to Take the First Step?
Share your Medical Reports with our Healthcare Managers Today and Get a FREE CONSULTATION, a Personalized Treatment Plan, and Complete Support from Arrival to Recovery.
Get Your Free ConsultationAreas We Serve
This resource has been thoughtfully prepared for patients from Canada who are considering medical treatment in India. We also welcome patients from the wider region in the countries mentioned below-
We regularly assist patients from:
- Canada
- United States
- Jamaica
- Bahamas
- Barbados
- Belize
- Guyana
- Saint Lucia
- Grenada
- Dominica
- Trinidad and Tobago
- Saint Kitts and Nevis
- Antigua and Barbuda
- Saint Vincent and the Grenadines
Many of the insights, treatment pathways, hospital recommendations, travel guidance, and patient support services described here are equally relevant and may be used as a reference when planning treatment in India.
From Canada to India: Your Complete Patient Support Guide
- Cancer Treatment & Surgery in India for Canadian Patients
- Cardiac Surgery in India for Canadian Patients
- Dental Treatment & Surgery in India for Canadian Patients
- Hip Surgery in India for Canadian Patients
- Knee Surgery in India for Canadian Patients
- Neurosurgery in India for Canadian Patients
- Spine Surgery in India for Canadian Patients
- Weight Loss & Bariatric Surgery in India for Canadian Patients
- Liver Transplant in India for Canadian Patients
- Kidney Transplant in India for Canadian Patients
- Prostate Cancer Treatment & Surgery in India for Canadian Patients
- Robotic Cancer Surgery in India for Canadian Patients
- Bone Marrow Transplant in India for Canadian Patients
- Brain Tumor Surgery in India for Canadian Patients
- Breast Cancer Treatment & Surgery in India for Canadian Patients
- Colorectal Cancer Treatment & Surgery in India for Canadian Patients
- Heart Valve Replacement Surgery in India for Canadian Patients
- Selecting the Best Laparoscopic and Robotic Myomectomy Centres in India for Canadian Patients